


Student name
Capella University
NURS-FPX9010 Doctor of Nursing Practice 2
Professor Name
Submission Date
Project Proposal
The problem of chronic disease treatment is an acute topic of discussion in the sphere of primary care provided in vulnerable population settings where healthcare access is low. The internal data of the site that is located in Rock Hill, South Carolina, show that 58 percent of type 2 diabetic patients had a hemoglobin A1C level greater than 9% in the past 12 months (Nurse executive, personal communication, July 10, 2025). The rate at the practicum site is extremely high compared to national rates, with one of the metrics being approximately 47 percent of diabetic patients with the HbA1c level more than 7 percent (CDC, 2024). Poor clinical outcomes in the clinic are a direct result of a lack of organized patient education programs, which serve a majority of uninsured patients. It can be seen that systematic interventions of self-management can make a great contribution to the clinical outcome, and they would enhance patient involvement in the chronic disease control process.
The identified gap is covered by the proposed quality improvement project through the implementation of the Stanford chronic disease self-management program (CDSMP) in nursing staff. The PICOT question is as follows: In nurses with adults with chronic disease such as diabetes (P), the application of the Stanford Chronic Disease Self-Management Program training (I) compared to the existing practice (C) after 12 weeks (T) has an impact on patient glucose control outcomes (O)? The CDSMP also offered evidence-based learning models, which increase the ability of nurses to provide effective self-management support to patients (Kerari et al., 2024). Programs of peer-led interventions are effective in improving patient self-efficacy and health behaviors in a wide range of health care environments (Bahari and Kerari, 2024). Through the project, the nursing personnel will have the necessary skills to enable them to achieve better results in managing diabetes among vulnerable groups.
Practice Problem
One of the fastest spreading public health concerns in the world is diabetes mellitus, which plagues millions of patients in various populations in the world. The International Diabetes Federation in 2021 put the global figure of adults with diabetes at approximately 537 million individuals, or approximately 10.5 percent of the population of the world (Hossain et al., 2024). By 2045, the cases of diabetes will have grown to 783 million, and healthcare expenditure will be more than 1,054 billion dollars (Kumar et al., 2024). Nearly half of all patients with diabetes are unaware of the health problem, and most of those who do not know it inhabit countries with low and middle income (Hossain et al., 2024).
In light of the increasing burden of diabetes, it is essential to address the evidence-based interventions to fill the gap in chronic disease management. It was revealed through the internal assessment of the project site that the performance of diabetes management among the population of patients treated by the clinic had serious gaps. Recent data collected over the past 12 months indicated that 58 percent of diabetic patients with type 2 diabetes possess a level of the hemoglobin A1c exceeding 9 percent (Nurse executive, personal communication, July 10, 2025). It is much higher than the national norms since, according to the statistics of the Centers for Disease Control and Prevention, approximately 47 percent of diabetic patients have an HbA1c of above 7 percent (CDC, 2024).
The clinic receives 80-100 patients in a week, with the majority being low socioeconomic individuals, who are either not insured or underinsured and require additional support in self-management. The susceptible populations experience an imbalanced chronic illness due to the non-optimal social determinants of health, including the inability to access healthcare and limited financial access (Hacker et al., 2021). The great disparity between the current outcomes and the evidence-based norms makes systematic intervention necessary to improve the skills of patient self-management and clinical outcomes.
Flawed Processes Leading to the Practice Problem
The most dysfunctional process that results in poor outcomes in managing diabetes at the clinic is the absence of structured patient education programs. Absence of self-management education, regularly set goals, and follow-ups, and the well-established system of treating chronic diseases, which involves individual visits to clinics, commonly characterize current care systems (Nurse executive, personal communication, July 10, 2025). The problem of medication adherence is quite a large issue in healthcare, and the patient-related factors, including the lack of information and disease-related knowledge, directly influence deteriorating self-management behavior (Kvarnstrom et al., 2021). Irresponsibility in communication, lack of trust in relationships between patients and healthcare providers, and insufficient support are decisive factors which impact medication adherence on the patient end (Kvarnstrom et al., 2021).
The chronic underfunding results in poor habits of monitoring, poor habits of lifestyle change, and poor habits of taking medication by patients with chronic diseases. The lack of structured interventions is one of the factors that leads to the course of inadequate outcomes and preventable complications. Literature that is available testifies to the fact that management of diabetes and chronic diseases, incorporating self-management support programs, is holistic, to provide the optimal patient outcome across all healthcare environments. The Covid-19 pandemic has impacted those people with chronic illnesses, with six out of every ten Americans having a chronic illness such as heart disease, stroke, cancer, and diabetes (Hacker et al., 2021).
Seven out of 10 causes of death in the United States are chronic diseases, which are the largest contributors to the annual cost of healthcare, or 3.8 trillion spent in the country (Hacker et al., 2021). Depression is intertwined with such chronic diseases as diabetes and hypertension, and the comorbidity is associated with the risk of mortality and reduced effectiveness of the intervention (Herrera et al., 2021). The number of people older than 50 years with at least a chronic disease will be increasing to 71.522 million in 2020 (99.5 percent) and 142.66 million in 2050 (Ansah and Chiu, 2023).
The use of new technologies: artificial intelligence, blockchain, and wearable technology incorporates the new paradigms of chronic disease management since they include patient-centered approaches (Xie et al., 2021). Polygenic risk scores have the potential to be more effective in predicting chronic disease prevention, although there are still barriers to their use in a broad population and clinical practice (Lennon et al., 2024). It has been demonstrated that effective self-management interventions can have a great impact on clinical results and reduce the cost of healthcare usage among vulnerable groups with chronic diseases.
Project Site
The large variety of populations requiring healthcare services requires a comprehensive infrastructure in healthcare, in which evidence-based interventions involved in the management of chronic diseases are well supported by the community. The site of the project is an outpatient primary care practice in Rock Hill, South Carolina, and has a heterogeneous patient base that includes many uninsured and underinsured patients who have lower socioeconomic statuses. The clinic functions as a direct primary care clinic with individuals primarily being out-of-pocket healthcare providers that provide an extensive variety of healthcare services, including preventive care, chronic illness care, urgent care services, health and women’s services, and telehealth services, in addition to aesthetic services.
The usual working hours in the institution are Monday to Friday, with a children and adult patient population of all ages and a staff population of six to eight, including nurse practitioners, medical assistants, administrative staff, and support staff. The physical infrastructure would include different examination rooms and certain procedures and chronic illnesses counseling zones, and telehealth equipment, with the help of which contact with a patient could be maintained in case of need. Having an adequate organizational infrastructure provides an appropriate background for the organization of the systematic quality improvement intervention to respond to the chronic disease management outcomes.
Rationale for Project Site Selection and Organizational Alignment
The key consideration of the selection of the appropriate implementation sites is the incorporation of the organizational preparation, nature of the patient population, and relevance to the evidence-based intervention requirements. The clinic manages an average of 80-100 patients in a week, which is a fair balance between the acute care visits, the follow-up of the chronic disease, and the routine health checks in the service area. The direct primary care model will offer an opportunity to spend more time with a patient and to have a flexible schedule that would make it easier to implement the educational intervention in a group. The particular interest of the clinic to help the uninsured and sub-insured population will be entirely aligned with the target population that will be most liable to the assistance of organized self-management education programs and peer support. The cultural diversity of the patient population presents the possibilities of peer learning of the culturally diverse population, and the developed infrastructure contributes to the utilization of the evidence-based methods of delivery. The need of the organization to improve the outcomes of chronic diseases is the best platform to utilize systematic quality improvement interventions.
Current Practice Limitations and Strategic Integration
The understanding of the existing organizational practices and strategic priorities contributes to the effective implementation of evidence-based interventions in the formulated clinical practices and processes. The clinic already possesses the fewest resources for patient education and generic chronic disease management regimes, yet the institution has not adhered to any systematic group education courses. The recent internal audits have recommended chronic disease management to be among the priority programs following the outcome evaluation, which indicated that there were significant disparities in the present patient outcome and national benchmarks. Leadership has enthusiastically supported evidence-based interventions as possible, using the suboptimal clinical outcomes (in particular, percentages of patients with uncontrolled diabetes needing immediate attention and systematic intervention strategies). Implementation of the strategic plans of the organization through the use of the Stanford CDSMP will involve the establishment of a systematic pattern of patient education, follow-up organization, and outcome improvement. The specified quality improvement initiative can be defined as the first methodological effort to address the gaps in diabetes self-management through the centralized, evidence-based educational initiative.
Project Population
The target population is identified when full knowledge of demographic, professional, and clinical responsibilities in the healthcare setting is presented. The project target population refers to the registered nurses who are the direct providers of care to the adult population with chronic illnesses, and on a narrower scale, type 2 diabetes, which may require constant care and educational support. They include the nursing professionals with various levels of experience in the management of chronic diseases, from a newly licensed practitioner to an experienced clinician with significant experience in the field of patient education. The research articles demonstrated that the nursing staff requires improved competencies in chronic disease education, motivational interviewing methods, and systematic self-management assistance to influence the patient outcomes positively (Beaudin et al., 2024). Within the framework of the work, the nurses are prone to addressing various clinical activities that include assessing patients, administering medications, planning care, and offering health education as they continue with their daily practice. The familiarity with the demographic and professional characteristics of the target population makes it possible to design and introduce the required intervention to adhere to the strategies.
Inclusion and Exclusion Criteria
Clear inclusion and exclusion criteria imply proper selection of the right people and consideration of the integrity of the project in the course of the implementation. The selection criteria will be registered nurses at the project site and direct person care duties with adults who have been diagnosed with type 2 diabetes. The participants should be willing to participate in the 6-week Stanford CDSMP training and commit themselves to using acquired skills in clinical practice. It has been proven that appropriately exposed to systematic training programs, caregivers demonstrate significant advances in the capability to interact with patients and the capacity to deal with chronic illnesses (Anderson et al., 2021). The exclusion criteria will include nursing staff who do not directly engage in caring for their patients, temporarily employed nurses or agency nurses with less organizational longevity, and nurses who will leave employment during the project implementation procedure. The criteria enable the dedication of the participants and can provide a comprehensive assessment of the efficacy of the interventions on the nursing practice and patient outcomes.
Minimum Sample Size and Site Capacity
The appropriate sample size can be established only depending on the statistical power, the possibility of data collection, and the organizational ability to contribute to the implementation of the intervention. The training intervention, which in this case will be the Stanford CDSMP plan, will include at least 15 registered nurses in the project. There are approximately six to eight nurses on site who provide direct care to patients, and the rest of the nursing care is provided by rotating shifts and part-time engagements, thereby increasing the number of participants. The capacity of the clinic to get 80-100 patients in a week is ensured to give the nurses sufficient clinical exposure and imitate the practice of self-management support skills acquired, and yield quantitative data of outcomes. The survival of the minimum number of participants was successful during the recruitment and retention exercise, as there was enough staff of nurses, high patient volume, and organizational assistance.
Evidence-Based Interventions
The rich literature should support the evidence-based interventions so that they can be consistent with both the identified practice issues and the clinical outcomes. Stanford CDSMP is a famous evidence-based intervention program to improve patient self-efficacy and health outcomes through the assistance of a structured educational program. However, the implementation setting is rather different in an international environment, and changes in self-efficacy and self-rated health scores and self-management behaviors in the community-based setting are statistically significant in Singapore (Hoong et al., 2022), and there is a focus-group-based study of the efficacy of CDSMP in Saudi Arabian cultural settings (Bahari and Kerari, 2024).
Nevertheless, both studies reached a similar conclusion that CDSMP is an effective intervention to improve the self-management skills of participants with the goal of making the patients more motivated to change behavior and more willing to communicate with the healthcare providers. Nevertheless, the emphasis on self-management skills and peer support of the program depicts the cultural flexibility, which is congruent with the different values of different populations and healthcare institutions. In systematic evidence, structured self-management programs have been demonstrated to be effective in managing chronic disease challenges in various populations. The self-management interventions are highly beneficial in the behavioral change process that is required to provide optimal management of chronic diseases and prevent complications. The meta-analysis of randomized trials recommended by Kim et al. (2021) indicates the small but significant effect size of self-management programs on physical activity, dietary habits, and health responsibility of individuals with chronic diseases.
Contrary to long-term intervention, short-term self-management programs that do not exceed a period of twelve weeks have been proposed to be particularly effective in modifying behavior in terms of physical activity and food habits (Kim et al., 2021). However, expert-based education has significantly more program impacts on food habits compared to peer-based interventions on a comparative basis to the non-intervention control groups. Nevertheless, Kim et al. (2021) found that the program’s impacts on stress management and smoking cessation were not significant, and this may reflect the differences in the behavioral domains. Nevertheless, with the limitations, self-management programs are applicable to mitigate various areas of behavior in chronic diseases. The complex behavioral changes have to be conducted with structured execution processes to ensure long-term transformations of the self-management behavior among the clients.
Technology-based self-management interventions are bound to offer an affordable and accessible personalized service of chronic disease management in different health care centers. The use of health and wellness mobile health apps to manage chronic diseases through self-management tools is not only trendy, but Wang et al. (2021) report that the applications were positively correlated with self-management behaviors in a variety of aspects. In comparison with the traditional approaches, mobile health application users involving mobile applications by adults were far more prone to utilizing personal health records, accessing healthcare providers with the help of technology, and making informed decisions regarding the management of chronic diseases (Wang et al., 2021). Still, Griffin et al. (2021) focused more on conversational agents rather than on the overall mobile applications and discovered indicators of progress on the tested scales, including the Patient Health Questionnaire and the Generalized Anxiety Disorder Scale.
Nevertheless, both technological approaches turned out to be successful, yet Lear et al. (2021) found that, in spite of the fact that digital health-related interventions did not significantly reduce the number of hospitalizations, they still could supplement primary care in the group of patients with multiple chronic disorders. Despite the fact that the technological platforms could be different, and the outcome measures could be different, the accessibility, usability, and preferences of the patient could be taken into consideration in order to maximise the engagement and outcomes of technology-enhanced interventions. It is possible to compare evidence-based interventions to identify the most appropriate strategies that would suit some practice problems, characteristics of the population, and organizational circumstances. The work of Hoong et al. (2022) and Bahari and Kerari (2024), based on the application of the traditional face-to-face self-management programs, proves the strong evidence of the implementation of self-efficacy and health behaviors improvement.
In contrast, digital health interventions are characterized by the special advantages of scalability and accessibility, and simultaneously do not lose effectiveness in promoting self-management behaviors and results. However, Griffin et al. (2021) noticed that conversational agents provide a two-way type of communication with automatic responses and evidence-based personalized reactions, which can be advantageous compared with traditional self-management interventions in the form of real-time personalization. Nevertheless, the study by Lear et al. (2021) has revealed that digital interventions are not always an alternative to traditional interventions, but face-to-face and digital support systems may be the most effective form of intervention. Although the technological progress that can be introduced with innovative strategies has its benefits, the traditional programs are admirable in the contact with other people and the culture-conscious practice. The attributes of population, level of technology literacy, availability of resources, as well as potentials of organisational infrastructure, also determine the choice of relevant intervention strategies.
Implementation Considerations and Practice Recommendations
The evidence-based interventions should be translated into clinical practice with a close consideration of the implementation fidelity, presence or absence of organizational readiness, and contextual factors that define the effectiveness of the program. The systematic reviews of barriers and facilitators to self-management of chronic diseases also present conflicting findings, as Nguyen et al. (2022) developed a systematic review where low health literacy, physical and cognitive decline, and the relationships with healthcare specialists were identified as critical issues of implementation. Contrary to biomedicine approaches, Kim et al. (2021) emphasized psychosocial phenotyping as the intervention-tailoring instrument has a high potential due to the principles of precision health and social determinants of health.
Nevertheless, the facilitators also depend on the studies, and Nguyen et al. (2022) mention family support, social networks, and religious beliefs as valuable resources. Nevertheless, the two schools of thought do not disagree about the importance of considering the differentiation of treatment methods, although Kim et al. (2021) suggested a more standardized method of phenotyping to maximize the precision of the intervention. Despite the existing methodological differences, it can be affirmed that the science of barriers and facilitators can guide the health professionals to establish the strength-based interventions that can be used to meet the needs of individual patients. It should be properly planned, engage the stakeholders, and constantly observed to deliver fidelity of intervention and optimal outcomes.
Alignment with Project Problem and Desired Outcomes
Practical interventions must demonstrate stable lines of logical relationship between research findings, guidelines of practice, and desired outcome changes expected. The Stanford CDSMP is directly related to the perceived disjunctions in the patient self-efficacy, self-management behaviors, and clinical outcomes that can be measured at the project site. However, on the one hand, where Hoong et al. (2022) demonstrated that health outcomes were enhanced in a communal setting in various ways, on the other hand, Bahari and Kerari (2024) emphasized such qualitative ones as elevated confidence and enhancement of communication with providers.
Nevertheless, the authors managed to show that the implementation of CDSMP is associated with positive results because the intervention improves self-management processes and quality of life among chronic patients. Nevertheless, the improvement process differs, and traditional programs pay more attention to peer support and experiences, whereas technology-enhanced ones pay more attention to accessibility and individuality. Regardless of such methodological variations, training the nursing staff on how the CDSMP delivery systems would work can enhance the capacity to provide quality self-management support to the patients, which would directly resolve the limitations that are currently present in practice. The combination of all the evidence demonstrates that there is a significant alignment of the proposed interventions, identified practice issues, and the planned clinical and behavioral outcomes.
Implementation Plan for Interventions
Step-by-Step Implementation Protocol
The fidelity to interventions can be systematic, and the implementation protocols may be applied in order to replicate evidence-based practice in diverse settings and groups of healthcare professionals. Extensive recruitment of registered nurses in the project site and providing direct care to adult patients with diabetes will introduce the practice. The participants will be selected, and baseline measures of self-efficacy, knowledge, and the present practices of self-management support will be made using the validated measures before the commencement of the program. The Stanford CDSMP training session will be delivered in six two-hour sessions every week, each session will be directed towards medication management, symptom monitoring, goal-setting strategies, communicating, and lifestyle change strategies. Research has revealed that the capacity of healthcare professionals to interact with patients and deliver chronic disease management services is enhanced by the implementation of structured training programs (Anderson et al., 2021). The post-training tests will come as a part of the program, and after 12 weeks of the test, to examine the retention and integration of the practices. The standardized implementation protocols enable the provision of the same level of intervention, which, in addition, facilitates the assessment of the program at the same level across diverse clinical environments.
Scholarly Leadership and Project Oversight
The main secret of proper project leadership is that the plan must be planned, regularly monitored, and able to be modified to operate in the complicated healthcare environment and retain intervention fidelity. Scholarly lead will spearhead the development of specific implementation schedules, training, participating in recruitment of the participants, and all the project implementation issues. The collaborative leadership styles allow applying both theoretical and clinical experience to achieve the greatest possible outcomes in the quality improvement projects (Silva et al., 2022). The working of the strategic partnerships with the preceptor will be scheduled based on regular meetings every two weeks to update them on the implementation progress, discuss the challenges emerging, and review the strategies based on the formative data. The academic head will update the stakeholders periodically, every month, by presenting data and seeking feedback to make sure that the organization is on course and is supported. Mechanical monitoring of data collection processes, discussion of formative outcomes, and development of progress reports will give the ability to detect the barriers to implementation at an early stage. The concept of scholarly leadership integrates evidence-based practice to provide sustainable changes in the outcome of managing diseases.
Preceptor Partnership and Collaborative Oversight
The successful quality improvement programs require a joint and partnership strategy that involves the merging of the academic knowledge, the clinical site knowledge, and corporate understanding. The preceptor can serve as the clinical mentor and strategist coach, providing the most valuable degree of location-specific advice regarding the character of the organizational culture, labor patterns, and connections with the stakeholders. The partnership activities will involve joint planning on how the implementation will be done, joint problem solving, whereby issues come up, and common communication with the organizational leadership on the project progress. A project leader should possess strong communication, strategic planning, and adaptive management abilities to operate within complicated primary care settings (Silva et al., 2022). Meeting with the preceptor every week during active implementation stages will also allow the scholar head to discuss the degree of the participants’ involvement, assess the compliance with the intervention, and make the modifications necessary. This will be done through constant collaboration to balance academic rigour and clinical feasibility, which will then be applied in translating evidence-based interventions into longer-term practice changes.
Internal and External Stakeholder Engagement
Incorporation of the stakeholders is among the most important aspects of successful quality improvement implementation that entails the strategic correspondence and decision-making throughout the project phases. The internal stakeholders entail the leadership of a clinic, nurse practitioners, medical assistants, the administrative staff, and the nursing staff who will be directly involved or affected by the intervention implementation. The internal stakeholders will be complying with new patient education procedures, systematic practices of self-management encouragement, and will be taken as part of data collection processes in the process of implementation. The organizational capability is the foundation of patient and family engagement to actively participate in the planning and improvement efforts of clinical clinicians, patient advisors, and collaborate with managers (Anderson et al., 2021). The external stakeholders are the patients who receive diabetes care services, the community health organizations, and the potential referral sources, which may have a better outcome in managing chronic diseases. The interaction with the stakeholders, which is strategic, makes it possible to align the organization and the constant support and high level of integration of evidence-based interventions into clinical practice routine.
Interprofessional Team Composition and Functions
Multi-disciplinary teamwork ensures that the quality enhancement process becomes effective since the meetup involves various knowledge, perspectives, and abilities that are required in the delivery of the holistic intervention. The nurse practitioner would serve as clinical champion and provide medical leadership, facilitate staff training on the protocols to treat diabetes, and help to incorporate self-management in the treatment plans. The medical assistant will have the responsibility of scheduling the patients, data collection instruments, documentation system, training, and follow up evaluation logistics. This will involve the administration staff to ensure the administration process and the stakeholders hold meetings, paperwork in the project, and ensure compliance with the organization’s policies and legal jurisdictions. Owing to the similarities in the decision-making and shared responsibility, the collective leadership styles contribute to improving the professional practice, healthcare outcomes, and personal welfare of the staff (Silva et al., 2022). The quality improvement coordinator will provide methodological skills, assist in the data analysis, be part of the outcome measures, and follow the implementation protocols, which are evidence-based. Overall, the availability of specific interprofessional roles will allow coordination of work, decrease redundancy, and utilize the resources available to the maximum in the course of project implementation.
Team Member Collaboration and Communication
There must be an established communication channel, regular coordination meetings, and clear expectations of the individual contribution to the project’s success in good interprofessional cooperation. The team members will be engaged in frequent coordinating meetings on a monthly basis, where they will discuss the implementation progress, challenges, observations concerning the effectiveness of the implemented interventions, and brainstorm on issues that arise. The execution will have the preceptor as a leader of team communication, put the clinical sites into context, bridge the academic and clinical concepts, and organizational alignment. The weekly email newsletters, document sharing systems, and the identification of the individuals to address the time-related concerns or questions will be the specific patterns of communication connected with the project.
The study demonstrated that interprofessional collaboration enhances the implementation of interventions by considering a broad scope of knowledge and mobilizing the efforts (Anderson et al., 2021). Each member of the group will be accountable in certain aspects, and will strive to achieve the organizational group goals by ensuring that one is present at all times within the team, all tasks allocated are accomplished within the required time, and that there is proactive communication. The systematic collaboration structures ensure the coordination of the implementation initiatives and assist in the attainment of the desired outcomes in the initiatives of chronic disease improvement.
Data Collection, Analysis, and Desirable Outcomes
Desirable Project Outcomes
The effectiveness of interventions is expressed in measurable outcomes that will undergo systemic assessment and allow to determine the success of the quality improvement project. The primary desirable outcome is the improvement of the glucose control in diabetic patients under nursing care by nurses who received the Stanford CDSMP training intervention. Specifically, the project will be aimed at reducing the percentage of patients with type 2 diabetes with hemoglobin A1c equal to or higher than 9 percent as a baseline through the reduction of the percentage to less than 45 percent in 12 weeks of implementation. Even when organized self-management programs were implemented, it was always supported that they have a huge beneficial effect on patient outcomes in diverse chronic diseases (Bahari and Kerari, 2024). The secondary outcomes include an improved nursing self-efficacy regarding the delivery of self-management education on diabetes, patient medication adherence, and patient participation in self-monitoring. To make the intervention objectively measure the effect on chronic disease management, specified desirable outcomes will be used as a guide to implementation activities and become possible.
Outcome Measurement Methods and Evaluation Criteria
The systematic outcome measurement should also have validated measures and assessment standards to measure the effectiveness of the intervention and to ensure the planned changes were made in the manner intended. Measurement of the outcome of patient glucose control will be in the form of the laboratory value of hemoglobin A1c by electronic health records at baseline, intervention, and 12 weeks following the intervention. The Self-Efficacy Scale used to evaluate nursing self-efficacy is the Self-Efficacy managing chronic disease scale that is a self-report scale consisting of six questions that measure self-efficacy in managing chronic diseases. The scale possesses a good psychometric property since its coefficients of Cronbach’s alpha of 0.91 to 0.93 are superb in internal consistency reliability across large populations. The tool was extensively used in its related chronic disease interventions of self-management, and the framework is responsive to change as a result of education programs (Hoong et al., 2022). The degree of medication adherence will be measured with the assistance of the Morisky Medication Adherence Scale, which is a validated instrument, being an eight-item instrument, and possessing a degree of reliability and validity in patients with diabetes. The validated measures will make it possible to evaluate the outcomes of the interventions with high quality and compare them with the previous evidence of other quality improvement initiatives.
Measurement Tool Validity and Reliability
Proper evaluation of the outcomes of interventions will also be ensured by the selection of psychometrically sound measurement instruments, which will enable rendering a credible interpretation of the results of a quality improvement project. The Self-efficacy scale of chronic disease management demonstrates the construct validity due to the significant levels of correlation with health behaviors, health status indices, and health care utilization patterns of the population with chronic diseases. The item validity occurred due to the examination made by the panel of specialists and cognitive interviewing of the patients who are representatives of different chronic conditions and demographic variables. In a batch of studies that establishes the same measurement properties over time, provided there is no change in health status, the test-retest reliability coefficients are more than 0.80. Self-efficacy scales are useful in evaluating change during the post-implementation period of the planned self-management education interventions within various healthcare settings (Hoong et al., 2022). The Morisky Medication Adherence Scale portrays concurrent validity and significant levels of associations with prescription refilling rates, electronic monitoring initiatives, and clinical outcomes in the process of managing diabetes. Formal licensing agreement has been secured as a license to utilize the instruments, and this ensures that the ethical standards of the study are upheld and that the proprietary measurement instruments are used in a proper manner.
Data Analysis Plan Using Descriptive Statistics
A proper statistical analysis of the findings enables the clear interpretation of the findings of the outcome and supports the findings of a quality improvement project in a meaningful way. The demographics of the participants and outcome measures will be described using all the continuous variables, including the means, standard deviations, median, range, and confidence intervals. Data analysis will be based on the calculation of percentages of patients with target glucose levels during the baseline period and post-intervention period of hemoglobin A1c values. The changes in nursing confidence will be determined by means and standard deviations of the scores of self-efficacy at each point of measurement time. An additional benefit of quality improvement projects is making the results data clear in the form of appropriate statistics that can be easily interpreted and used to make a clinical decision (Hoong et al., 2022). The percentages of medication adherence will be determined as the percentage of those who have high adherence based on the established levels of scoring the Morisky scale. The Descriptive analyses would aid in establishing the background within which the impact of the intervention may be interpreted and communicating the results to the stakeholders and the healthcare community in general.
Data Presentation and Outcome Dissemination
Data presentation will help to understand the stakeholders and will help to make evidence-based decisions about the sustainability and development of the quality improvement initiative. Frequency distributions of categorical variables, including the demographics of the participants, the type of patient diagnosis, and the type of compliance to the new change, will be the categorical variables to be calculated to describe the sample composition in detail. The presentation of changes in outcome measures will be in a table format of the baseline and post-intervention values, and values at 12-week follow-up, with the corresponding percent of improvement. The indicators will be shown in graphical charts comprising bar charts, line graphs, etc indicating the changes in percentages of hemoglobin A1c, self-efficacy scores, and adherence rates over time. Proper data display allows the stakeholders to be better engaged and the transfer of quality improvement results into sustainable practice changes (Kim et al., 2021). The summary statistics will be captured into detailed reports to the organizational leadership, the clinic staff, and other external stakeholders, which will contain the key findings and implications. The systematic data analysis and presentation approach enables one to support the free flow of the project results and make informed decisions related to the adoption of the interventions and the sustainability.
Conceptual Model
Plan-Do-Study-Act Model Overview
Quality improvement models provide a theoretical construct of providing evidence-based interventions and conducting the evaluation in a clinical practice setting. Plan-do-study-act (PDSA) model is one of the widely recognized cycles of quality improvement that has been designed as iterative and is utilized to test the changes before the massive implementation. The PDSA cycle consists of four phases, which follow each other, i.e., planning of the change as well as defining goals, small-scale implementation of the change, exploring the outcomes and analysis of data, and performing action on the findings to enhance the intervention or expand it.
Quality improvement programs based on PDSA can enable the continuous improvement of the interventions using the systemic testing, evaluation, and adjusting the interventions depending on the field experience of implementation. The PDSA model permits the expeditious cyclic procedures of enhancement that facilitate acquisition and assimilation of the evidence-based practices into normal clinical practice in the long run. The results of the systematic quality improvement methodologies are the rigorous assessment of the research evidence and its translation into the improvements that are to be maintained in practice.
Connection of the PDSA Model to Project Goals and PICOT
Conceptual frameworks must be the basis of implementation and evaluation that would follow logically the objectives of the project, research questions, and the expected outcomes to deliver the desired outcomes. The PDSA model has direct correspondence to the project PICOT question that begs the question of the impact of Stanford CDSMP nurse training on patient glucose control outcomes in 12 weeks compared to the current practices. The plan phase involves developing elaborate training processes, setting the level of baseline control of glucose, and the criteria of success based on the project objectives.
The Do stage will involve the implementation of the 6-week CDSMP training program among 15 registered nurses and the introduction of the application of the learned skills of self-management support to the clinical practice. The PDSA model demonstrated the possibility to improve the goal-setting process of the providers to self-management of the chronic diseases with quantifiable changes in the healthcare delivery practices associated with the improved outcomes (Krishnappa et al., 2022). The stage of the Study will involve the analysis of patient hemoglobin A1c levels, self-efficacy levels of the nurse, and medication adherence rate following intervention. The framework provides an iterative formalization of the refinement and makes sure that the project implementation is a continuous quality improvement.
Framework Guidance for Project Implementation
Conceptual models are an excellent template for systematic implementation of the project, making it possible to make systematic decisions and to make continuous improvements throughout the process of the quality improvement initiative life cycle. The PDSA model will be used to introduce initial small-scale testing to five nurses and further train the rest of the colleagues (15 nurses) on the given program. The knowledge that will be obtained during the initial cycles will determine the modification of the training contents, mode of delivering the training, timing, and support mechanisms before they are adopted widely. The application of PDSA cycles provides the necessary information to the teams to make the decisions about further spreading of the program and the strategies to engage the population (Pullyblank et al., 2025).
The PDSA cycle’s cyclic nature allows identifying and overcoming the barriers in the implementation process, optimizing and reorganizing the aspects of the interventions, and distributing the resources between the stages of the project. Working with lessons learned in each cycle will lead to constant improvement, high levels of intervention fidelity, and the probability of success in the outcome of glucose control and nursing competency. The framework allows dynamic implementation strategies, which respond to the emerging challenges with a capability to remain in touch with evidence-based best practices.
Application of the PDSA Model in Similar Chronic Disease Management Projects
The usefulness of the PDSA approach in enhancing the results of self-management of chronic illnesses within different healthcare facilities is evidenced by the evidence of similar quality improvement initiatives. The PDSA model was successfully applied to increase the frequency of goal-setting activities documentation among the resident providers by the baseline and 33 percent in the serial cycles, which included reminders, discussions with the faculty, educational videos, and policy changes (Krishnappa et al., 2022). The Living Well program has implemented the rapid quality improvement cycles based on the PDSA approach to implement the self-management program recruitment, referral, and coordinating systems within a six-county rural area (Pullyblank et al., 2022).
Disease self-management programs using PDSA cycles and evidence-based approaches resulted in the involvement of more than 750 people in workshops and increased involvement in primary-care clinician referrals and structural changes embedded in healthcare systems (Pullyblank et al., 2022). The PDSA cycles were advantageous to health educators regarding the necessity to consider the ways to expand the program reach and the possibility to engage new populations of interest in self-management in chronic diseases (Pullyblank et al., 2025). The applications that have been winning demonstrate the applicability and relevance of the PDSA methodology to the complex needs in chronic disease management, as is the situation with the current project focus.
Methodology, Budget, and Ethical Considerations
Project Methodology and Design
The quality improvement projects shall be clear with methodologies that define the design features, assumptions, and the protection measures of the human subjects. The proposed project will adhere to a quasi-experimental pre-post design, according to which one intervention group of 15 registered nurses was to complete the Stanford CDSMP training. It is assumed in the project that the nurses possess the fundamental motivation to enhance their expertise in diabetes management, patients will be engaged in the self-management assistance endeavors of the trained nurses, and the organization’s infrastructure must be favorable to the systematic execution. The quality improvement initiative benefits from having gainful systemic implementation plans to achieve consistency in delivery and to have an opportunity to see substantial evaluation of intervention effectiveness (Krishnappa et al., 2022).
The protection of human subjects will be attained through voluntary participation, an informed consent procedure, and proper institutional review board consultation to draw the line between quality improvement and research categories. The rigorous evaluation of the intervention outcomes in the methodology is ensured with the help of standardized data collection procedures, validated measures, and the systematic procedures of documentation. The detailed methodology planning has formed the basis of successful implementation and reasonable interpretation of the findings of quality improvement projects.
Project Limitations and Mitigation Strategies
It is possible by identifying the constraints of a project, creating the related mitigation strategies, and interpreting the results in a realistic manner, depending on the contextual constraints. The single-site design cannot be used to generalize to other primary care settings where patients have a different patient population, organizational complexities, or resource endowment. The limitation on the power of statistics and the ability to determine small effects or relationships between the components of the intervention can be the small sample size of 15 participants in the nursing population. In order to introduce evidence-based programs to different settings, it can conduct sustainable adaptation and capacity-building activities to adapt to the contextual barriers and optimize the functionality of the interventions (Pullyblank et al., 2022).
Such issues as potential participants dropping out will be minimized through the creation of flexible schedules, constant engagement plans, awarded further education, and organizational support. The problem of selection bias will be eliminated through the recruitment of all the eligible nursing personnel and a clear description of the inclusion criteria, characteristics of the participants, and the non-participation. Mitigation strategies ensure the best quality of data, improve the intervention fidelity, and achieve a valid interpretation of results within the identified limitations.
Budget Considerations and Resource Allocation
The thorough budget planning would offer adequate resource allocation and contribute to the introduction of evidence-based quality improvement interventions on a sustainable basis in clinical settings. The project budget indicates the Stanford CDSMP training resources of 500, which will involve the facilitator guides, participant guides, and other learning resources. The largest portion of the budget is the staff time, as 12 hours of training time per nurse costs 180 hours and 20 hours of project coordination, data collection, and analysis activities. Multi-sector partnerships require continuous capacity-building with partners and efficient utilization of the assets of the healthcare system to maximize the program implementation (Pullyblank et al., 2022). Information technology assistance of 1,000 dollars will be required to support the usage of electronic health records to modify the process of glucose recording. Other costs include training facility, training audio-visuals, training refreshments, and printing evaluation equipment, which is approximately 300 dollars. Budget planning is extensive, and it forms fiscal responsibility and availability of resources that are required during the implementation phase of the quality improvement project.
HIPAA Compliance and Data Security Protocols
The key ethical issues related to the quality improvement under the covered health information provision include the privacy of patients and data security. All the patient data with hemoglobin A1c values, data on medication adherence, and demographic data will be de-identified with the assistance of a unique numeric identifier that will not be linked with personal information. The data files will be stored in the encrypted password-controlled computers, which will be accessible to the authorized members of the project team, who may receive the certification of the HIPAA training as well. The quality enhancement initiatives must encompass stringent data protection measures in order to be kept confidential and not to lose credibility among the participants and the healthcare organizations (Krishnappa et al., 2022).
The hardcopy of the identifiable information will be locked in the filing cabinets in the secure office locations, and access will be restricted to only necessary personnel. The data transmission method will be done through secure and encrypted email software or password-protected file-sharing systems, which will be approved by the information technology security policies of the organization. All in all, data safety precautions will be observed to guarantee that the federal regulations are observed, the privacy of the participants, and the ethicality of the project implementation.
Project Timeline
Implementation Timeline and Work Plan
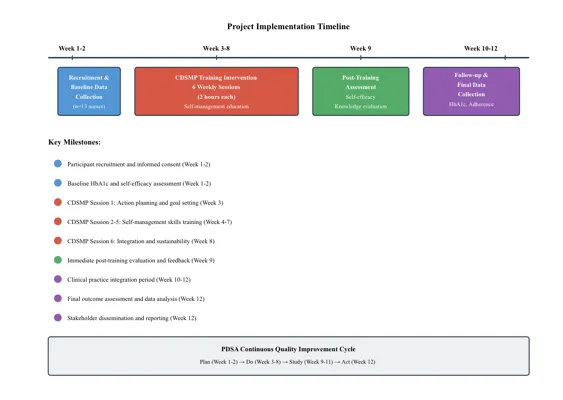
Systematic projects are planned out in brought schedules by activities that have to be implemented, by whom, and by what milestones should be achieved throughout the process of the quality improvement endeavor. The 12-week implementation will consist of the recruitment of the participants, data collection during the baseline, 6 weeks of training in Stanford CDSMP, post-training assessment, and follow-up evaluation. The first and second weeks will be spent on recruiting the participants, obtaining informed consent, and baseline data collection in case of hemoglobin A1c and a self-efficacy test. The processes of quality improvement are very fast and, as a result, the constant improvement is enabled through the systematic planning, application, review, and adaptation of the experiences occurring in the real world (Pullyblank et al., 2025).
The six-week CDSMP training intervention involves week’s three to eight, during which a two-hour training session is offered once a week, and a summative post-training test is conducted at the end of the six weeks. The rest of the implementation of the learned skills to the clinical practice, as well as data collection, preliminary analysis, and the reporting of results to the stakeholders, will follow in weeks 10-12. Top-level planning of timelines assists in undertaking implementation activities in coordination and aids in the methodical achievement of quality improvement goals within set durations of time.
Figure 1
Project Implementation Timeline
Practicum Hours Plan of Action
The practicum hours are structured in such a way that the hours provide an encompassing process of experiential learning in accordance with the goals of the doctoral competencies and professional development in the entire program. The Doctor of Nursing Practice program assumes 1,000 hours in practicum, which is distributed over the courses of the doctoral advanced program, including the project planning, implementation, evaluation, and dissemination activities. The practicum experiences include direct patient care experiences, quality improvement project execution, stakeholder engagement, personnel education, data gathering and data analysis, and academic publication. Long-term engagement of clinical locales, systematic introduction of evidence-based interventions, and assessment are part of quality improvement initiatives to achieve meaningful outcomes (Krishnappa et al., 2022). All courses will have their hours documented using standardized tracking systems, and the preceptors, together with faculty mentors, will often check on the hours. Proper planning of the practicum can ensure that required hours are met and the required skills in advanced nursing practice and academic leadership are obtained.
Table 1
DNP 1,000-Hour Practicum Plan of Action
DNP 1,000 Practicum Hour Plan of Action | |||
Transfer Hours – Please indicate if they have been approved or submitted. | |||
DNP Project Hours | Total from core courses. | ||
Hours from NURS 9000. | 100 | ||
Projected hours from NURS9010. | 100 | ||
Practicum Hours: Include a description of the activity and estimated hours. Add additional rows as needed. | Course | Activity | Planned hours |
NURS9020 | Literature review and evidence synthesis | 50 | |
Site assessment and organizational readiness evaluation | 40 | ||
Stakeholder meetings and needs assessment interviews | 10 | ||
Project charter and implementation plan development | 40 | ||
IRB consultation and ethical review documentation | 20 | ||
Preceptor meetings and project planning sessions | 30 | ||
NURS9030 | Participant recruitment and informed consent procedures | 30 | |
Baseline data collection (HbA1c, self-efficacy, adherence) | 40 | ||
CDSMP facilitator training and certification | 50 | ||
Training materials and resource development | 40 | ||
EHR coordination and system modifications | 30 | ||
Staff education sessions and implementation preparation | 40 | ||
Preceptor consultation and progress monitoring | 30 | ||
NURS9040 | CDSMP training delivery (6 weekly sessions × 2 hours) | 60 | |
Participant support and coaching between sessions | 50 | ||
Observation of nurse implementation in clinical practice | 40 | ||
Formative data collection and PDSA cycle adjustments | 90 | ||
Stakeholder update meetings and progress reporting | 40 | ||
Documentation and intervention fidelity monitoring | 30 | ||
Preceptor supervision and mentorship sessions | 40 | ||
Total Practicum Hours | 1000 | ||
Conclusion
The quality improvement project will address the wide gaps in diabetes self-management support that exist in the project site by applying the Stanford CDSMP training to a group of 15 registered nurses dealing with patients with diabetes type 2 diabetes among adults systematically. It is expected that the project will enhance the current 58% baseline of patients with A1c above 9 percent to below 45 percent in 12 weeks through the enhancement of nursing competencies of self-management education and support based on evidence. The intervention may be implemented with the assistance of the Plan-Do-Study-Act model through six training sessions each week and a systematic review of the patient outcomes in glucose control, nursing self-efficacy, and medication adherence with the assistance of validated measures. Additionally, patient education strategies focusing on lifestyle modification and dietary adherence will be reinforced to support long-term glycemic control outcomes. The 1,000 practicum hours will be spread between the advanced doctoral courses that will offer effective exposure to all the phases of the project, including planning, implementation, evaluation, and scholarly dissemination processes. The introduction of appropriate changes will result in sustainable modifications to the practices of chronic disease management and will provide valuable evidence about the issue of nurse-led self-management intervention in the primary care setting in vulnerable populations. The project will become an essential step in the development of the process of diabetes care related to the use of evidence-based nursing practice and systematic quality improvement instruments.